



home
>
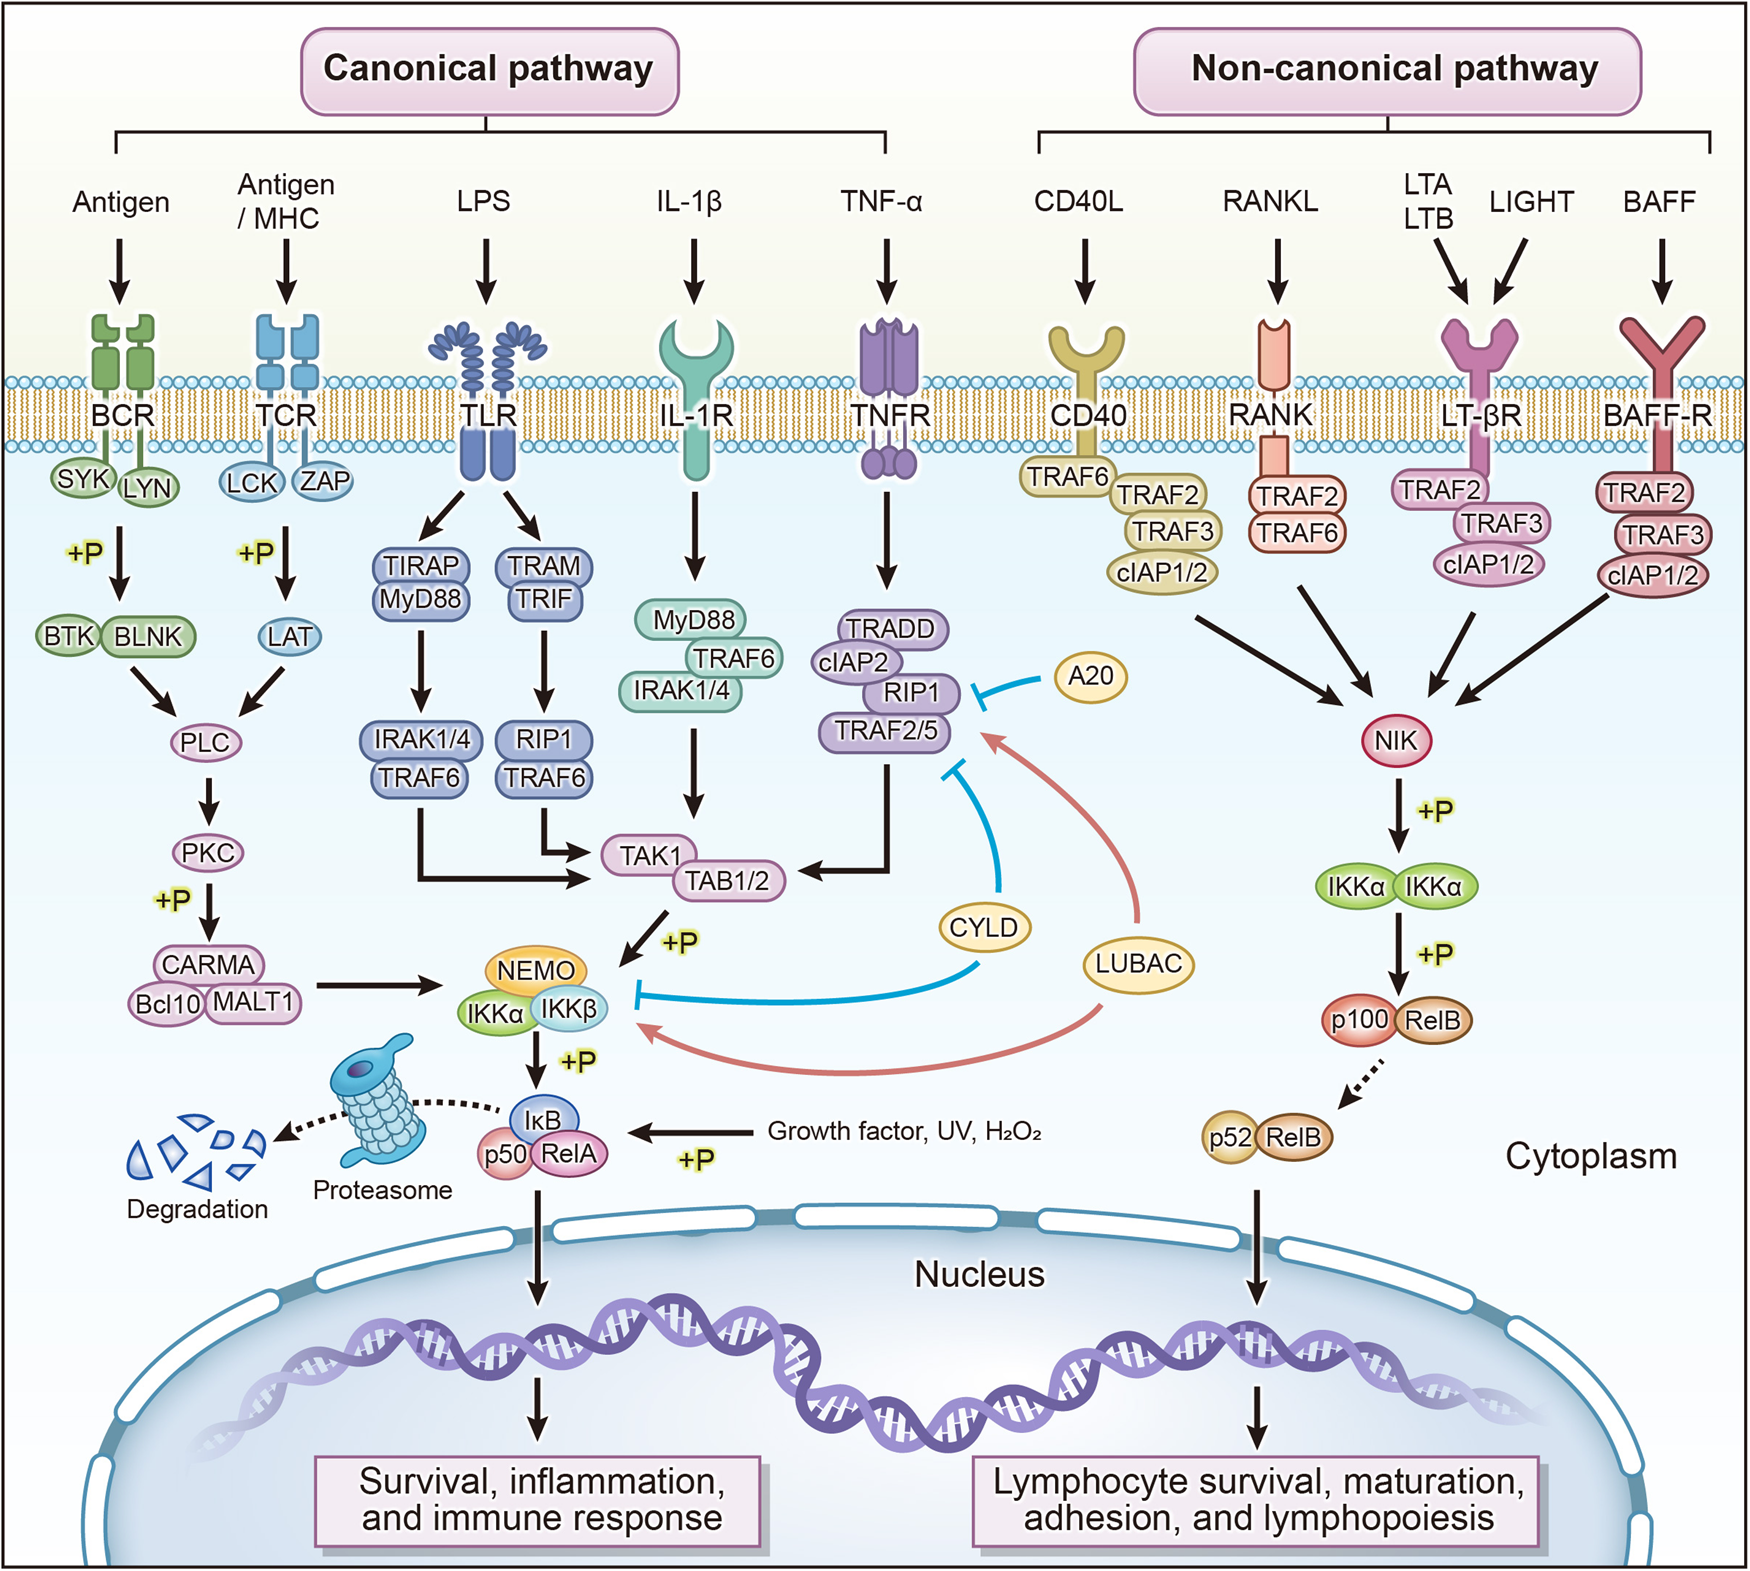
ghk-cu downregulates nfκb NF-κB in biology and targeted therapy: new insights and translational implications BPC-157 COA, SKU Specifications
>
ghk-cu downregulates nfκb NF-κB in biology and targeted therapy: new insights and translational implications BPC-157 COA, SKU Specifications


download picture
description
ghk-cu downregulates nfκb NF-κB in biology and targeted therapy: new insights and translational implications BPC-157 COA, SKU Specifications

Shopping security
product description
Why choose thelockerguy wholesale?
ghk-cu downregulates nfκb NF-κB in biology and targeted therapy: new insights and translational implications BPC-157 COA, SKU Specifications
BPC-157 COA, SKU Specifications & Starting Prices | PeptiCore
Mechanism Overload of the extensor mechanism complex (quadriceps, quadriceps tendon, patella, patellar tendon, tibial tubercle) More likely to occur with knee flexed to 60 degrees, given most force on tendon at this angle (Matava 1996) Epidemiology Uncommon injury: Females Age: 20s and 30s most commonly More often unilateral, but bilateral patellar tendon rupture has been documented (Matava 1996) Predisposing Factors (Volpi 2016) Previous surgery Patellar tendinopathy SLE Rheumatoid arthritis Chronic renal failure DM Physical Exam Loss of extensor mechanism (ability to extend at knee joint) Hemarthrosis, swelling, tenderness Palpable defect inferior to patella Patella alta (elevation of patellar height) Inability of unassisted weight bearing (Volk 2014) Injury Classification Partial tendon rupture – Extensor mechanism intact Complete tendon rupture – Loss of extensor mechanism Tendon avulsion from inferior pole of patella May include bony fragment when associated patellar fracture (McMahon 2014) Mid-tendon rupture Tendon avulsion from tibial tubercle May include bony fragment when associated tibial tubercle fracture Xrays Trauma knee series: AP, lateral, obliques and can consider sunrise/tunnel views if indicated Xray cannot visualize tendon, but may provide other evidence of tendon rupture as shown below Ultrasound Can aid in diagnosis at bedside using longitudinal view from inferior patella to tibial tuberosity Normal tendon structure can be identified as multiple parallel echogenic lines Rupture can be identified as a hypoechoic break with surrounding edema MRI Gold standard for diagnosis Usually unnecessary in ER and can be obtained as out-patient if needed Emergency Department Management Partial tendon rupture Usually treated non-operatively Knee immobilizer and crutches ( non-weight bearing in immediate period ) Orthopedic follow up – graded weight bearing as tolerated for 3-6 weeks (Khan 2005) Complete tendon rupture Usually treated with operative repair Prompt follow up necessary (within 1 week) Non-weight bearing with knee immobilizer and crutches Shorter time to surgical repair was associated with better outcomes of recovery – lower incidence of quadriceps weakness and incomplete knee flexion (Matava 1996) Indications for immediate Orthopedic consultation Any associated fracture (e.g
Color:Emerald Green / Gold - Velvet
NAD+ is not intended to diagnose, treat, cure, or prevent any disease
ghk-cu downregulates nfκb NF-κB in biology and targeted therapy: new insights and translational implications BPC-157 COA, SKU Specifications
Item no
:
8630754384
US$ 24.77
Pay in 4 interest-free payments of $6.19 Learn more
Min. order:
1piece
Shipping Estimate
USA
- USA
- CAN
- USA
- CAN
Ships within 48 hours · Estimated delivery Oct 14 - Oct 19
US$40
Get nowSign up to your membership to get coupons up to
15%
Get nowOpportunity to enjoy order discount up to 15% off
Please add the products
Shipping Notes
- Free Standard Shipping on $100+ Orders to the USA.
- Except Preorder products are shipped in 48 hours.
- Delivery to the USA:
- Standard Shipping : 3-10 business days
- If time is of the essence, please consider selecting expedited delivery for faster service.
Exchange/Return Notes
- We offer a 30-day return/exchange service after receiving.
- Final sale items are not eligible for returns or exchanges.
- To process your return/exchange, please contact us at [email protected]
- Please click here for more details>>> Return & Exchange Policy
Frequently Asked Questions for ghk-cu downregulates nfκb NF-κB in biology and targeted therapy: new insights and translational implications BPC-157 COA, SKU Specifications
How can I make a useful comparison table for several products?
Keep missing information visible instead of filling it with guesses. Use the table to support judgment rather than replace it.
How can I separate essential requirements from preferences before shopping?
Consider whether an acceptable alternative could meet the same purpose. Avoid allowing a short deadline to erase an essential requirement.
What should I remove before sharing an order screenshot publicly?
Use a cropped view when it fully supports your intended point. Keep enough context to avoid misrepresenting the information shown.